What the NIH cuts mean for global health - an update
By Dr Paul Barnsley 25 September 2026
An update on the scale of the NIH cuts
By Dr Paul Barnsley, Technical Lead at Impact Global Health
In November last year, we published a report, titled ‘State of Disunion’, which broke down the likely impact of cuts to global health R&D made by the US government. One of the key questions was the status of grants made by the National Institutes of Health (NIH), the primary US agency in charge of public health and biomedical research and by far the largest source of global health R&D funding in the world – responsible for 37% of all global health R&D funding since we began tracking it in 2007.
In last year’s report, we predicted that the various US global health funding cuts – the shutdown of USAID, terminating grants thought to be linked to diversity, equity and inclusion (DEI), ending funding for mRNA vaccines, new policies on overheads and overseas awards, disruptions to grant awards – would amount to a 2025 reduction of around US$880m, or 18%.
Complete 2025 data will be available in November following this year’s G-FINDER survey. In the meantime, though, we have been able to update some of the data in last year’s report. The impacts we can now observe show that the US funding system is surprisingly resilient in the face of deliberate cuts to funding but worryingly exposed to disruptive policy change.
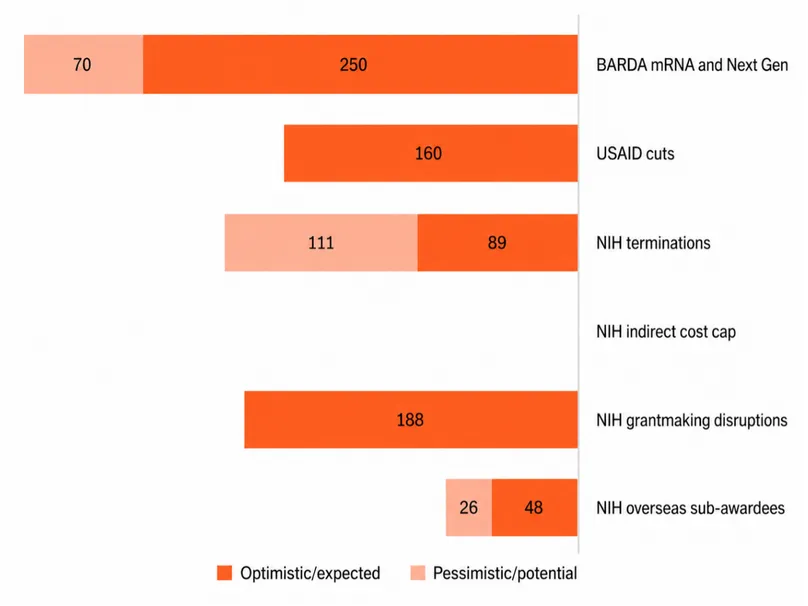
One of the policies we included in our $880m headline estimate – a cap on NIH overhead rates which would have directly reduced the value of most of its grants – was struck down by the courts and never went into effect. But another proposed change – the restriction on awarding part of a grant outside the US – which we had thought was unlikely to take effect in practice, did end up causing wider disruptions despite the theoretical workaround offered by the NIH. These two opposing mistakes partly balanced each other out, but the net result is somewhat good news: net overall funding likely dropped by about $125m less than we had expected.
The hardest thing to predict last August was whether the NIH, which had been disrupted by a series of staffing and policy changes, would manage to actually issue its usual number of grants by the 30 September 2025 deadline. The latest evidence suggests that they did, but only by issuing a smaller number of bigger-than-usual grants. Projecting from the most up-to-date NIH figures, we estimate that this shift to fewer, but larger grants has led to a 16% drop in NIH funding for global health R&D – only a little lower than the 18% drop we predicted last August.
These estimates remain uncertain, though, both because the NIH’s figures themselves seem unusually volatile this year, and because we’ve assumed a constant share of global-health-relevant grants from those that match our broad keyword searches.
The net effect of our latest projections – no cut to overheads, an unexpected impact from blocking awards outside the US, slightly less disruption than we predicted at the NIH – is that overall US government funding probably dropped by about $150m less than we predicted last year, by about $730m, rather than the $880m we had projected.
Relative to last year’s report, this is modestly good news – a cut in US public funding of just over 15%, rather than the 18% we believed we were facing. Relative to a world where US funding for global health continued its typical year on year growth, though, the news remains shockingly bad: a $730m cut in R&D funding would, by itself, reduce global funding by more than 9%, taking it to its lowest level since the COVID pandemic.
Forecasting future NIH funding patterns
Looking to the future, overall congressional funding for the remaining US Government funders of global health R&D remains robust: appropriated BARDA funding is up very slightly from 2025, despite the cessation of its work on mRNA; the deep cuts to NIH funding outlined in last year’s Presidential Budget Request have not been enacted; and the State Department, home of what remains of USAID, has been allocated $50m for ‘Prevention, Treatment, and Response’, alongside Congress-mandated continued funding for CEPI.
We do, however, expect the impact of restriction on overseas NIH awardees to mostly continue throughout 2026, as the new mechanism for approving foreign awardees gradually starts to operate as intended.

And the NIH is once again struggling to issue grants at the pace it needs to meet its 30 September deadline for obligating funds. So we expect another year of last minute allocations of larger-than-usual amounts, with recipients receiving funding intended to cover more years than normal, with an uncertain impact on global health R&D: last year’s rushed NIH grantmaking seems to have led to reduced global health R&D funding, but we have no way of knowing whether that was just bad luck, or an inherent feature of trying to issue a lot of funding while trying to beat a deadline.
So in part, US public R&D funding proved more resilient than either its opponents or its supporters imagined. In the absence of explicit congressional support for reducing funding, many cuts were successfully challenged in court – including more than half of the initial wave of NIH grant terminations.
The broken funding plumbing
More effective in disrupting funding, it turned out, were changes to the internal plumbing of the funding system. A communication freeze that prevented publication of required notices and added compliance checks generated a yearlong shortfall in NIH funding even without a change to its budget; and a new way of structuring overseas awards instead ended up mostly defunding them for more than a year. Understanding the future direction of funding requires looking beyond headline budget proposals to how the integrity of the system might be compromised.
But the most serious threat to global health R&D might not be further cuts, but a change in who decides what gets funded. The US Government’s Office of Management and Budget has proposed a government-wide system in which scientific peer review would be treated as merely advisory, with political appointees having the final say over grant announcements and awards, and existing grants subject to termination when they ‘no longer serve federal priorities or the national interest’.
Recent reports appear to corroborate this, suggesting the creation of ‘a new external committee with the power to veto awards in the nation’s vast biomedical research portfolio’ which are judged not to White House priorities. If adopted, rules such as these would turn last year’s scuffles over DEI and mRNA into a permanent feature of the grantmaking process – leaving researchers unsure if their committed funding will continue from month to month, and rendering even congressionally mandated research funding vulnerable to political screening beforehand and politically-motivated cancellation afterwards.